


THE IMPACT OF PH-ILD
Pulmonary hypertension may be present at any stage of ILD, even at diagnosis2-4

Up to 15% of patients with early-stage IPF have confirmed PH.2-4

As ILD advances, PH frequency rises.2
In patients with advanced and end-stage IPF, PH prevalence can rise beyond 50%.2*
- Up to 86% of patients with IPF may develop PH by the time of lung transplant.5
Check for PH at diagnosis of ILD, when you review your patient's CT, and during routine follow-ups.3,6-8
*Composite graphical representation of the mPAP distribution observed across multiple studies in patients with IPF.
Regardless of hemodynamic severity, PH significantly impacts prognosis9†
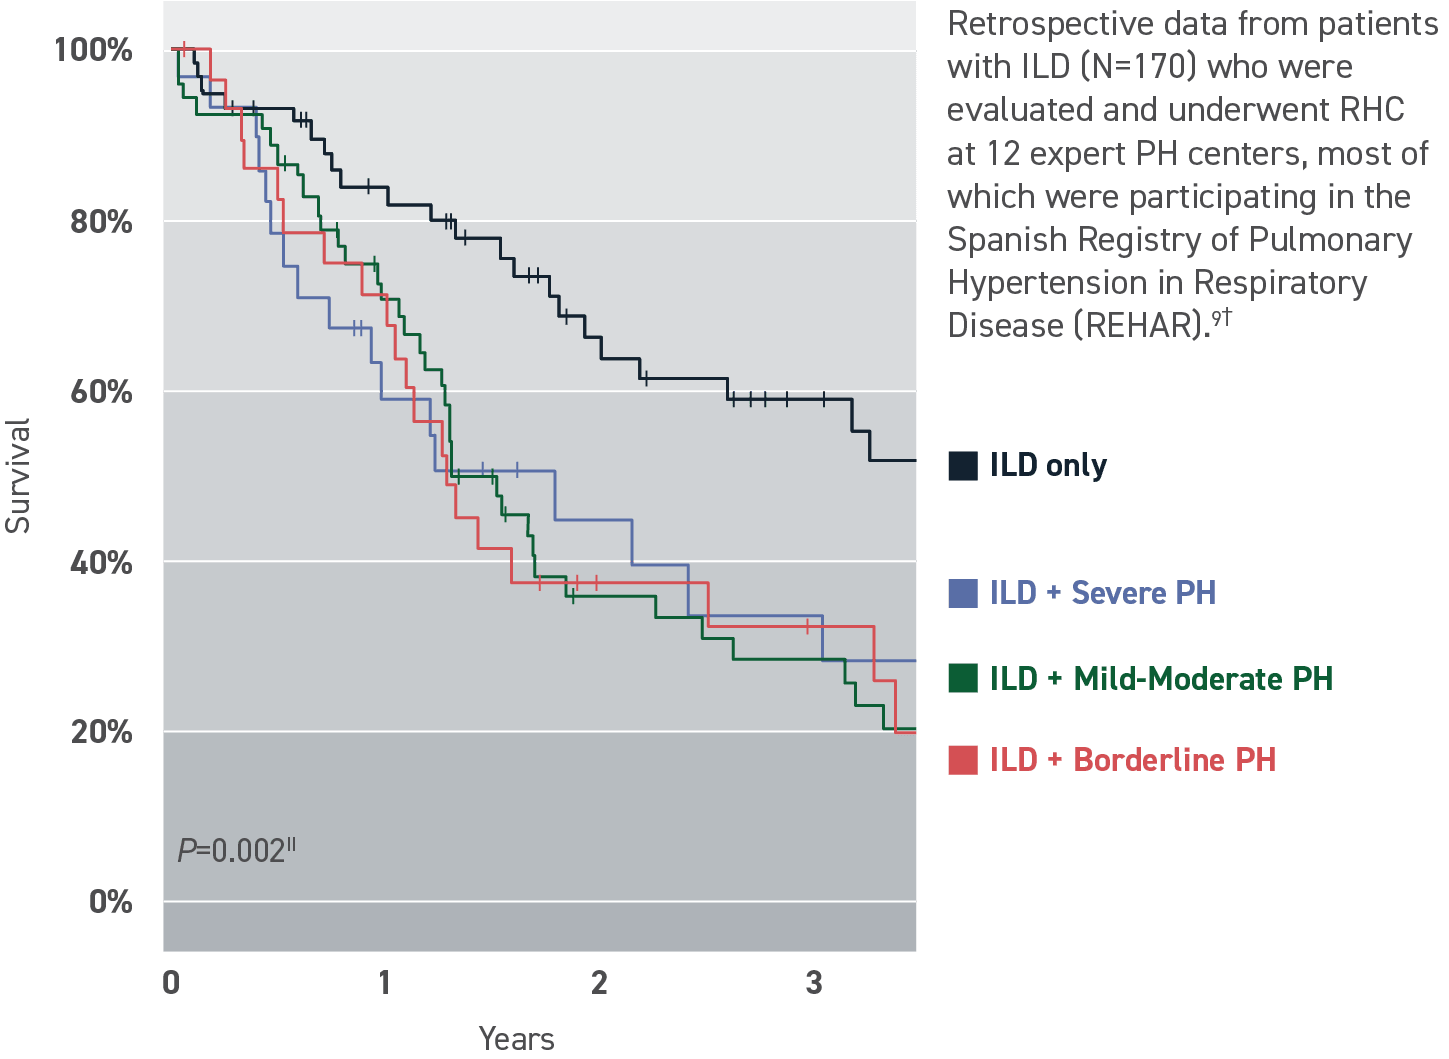
In a separate analysis, there was no difference in the risk of death for patients with a PVR >5 WU compared to those with a PVR ≤5 WU.9
Any PH—no matter how mild or severe—significantly worsens your patient's prognosis.9,10
†Patients with CPFE, left heart disease, or who had undergone lung transplant were excluded. ILD diagnoses (N=170): 74% IPF, 15% nonspecific interstitial pneumonia, 8% hypersensitivity pneumonitis, and 3% other.9
‡Patients were divided into 4 hemodynamic subgroups based on the 2018 WSPH definitions for Group 3 PH, with patients falling within the then newly lowered mPAP threshold range (21-24 mm Hg) separated into their own subgroup: ILD only (No PH), mPAP <21 mm Hg or mPAP 21-24 mm Hg and PVR <3 WU; Borderline PH, mPAP 21-24 mm Hg and PVR ≥3 WU; Mild-Moderate PH, mPAP 25-35 mm Hg and CI ≥2.0 L/min/m2; and Severe PH, mPAP ≥35 mm Hg or mPAP ≥25 mm Hg and CI <2.0 L/min/m2.9
§Median values at baseline: ILD Only = mPAP 19 mm Hg; PVR 1.8 WU (n=59); ILD + Severe PH = mPAP 41 mm Hg; PVR 7.7 WU (n=30); ILD + Mild-Moderate PH = mPAP 29 mm Hg; PVR 4.7 WU (n=52); ILD + Borderline PH = mPAP 23 mm Hg; PVR 3.5 WU (n=29).9
||The P value pertains to comparing survival in any PH group vs the No PH group at 3 years.9
ILD can cause changes to the lung microvasculature2,11,12
PH-ILD pathophysiology is multifactorial. Pulmonary vascular changes that occur due to ILD may include2,11,12:

Aberrant angiogenesis, including abnormal vascular connections in fibrotic tissue and abnormally dense capillary networks in areas with minimal fibrosis
AND
Vascular remodeling throughout the lungs, including thickening of arterial walls and occlusion of pulmonary venules
Progression of vasculopathy leading to PH-ILD can occur at a different rate than progression of fibrosis or decline in FVC.9,11,13
CI=cardiac index; CPFE=combined pulmonary fibrosis and emphysema; CT=computed tomography; FVC=forced vital capacity; ILD=interstitial lung disease; IPF=idiopathic pulmonary fibrosis; mPAP=mean pulmonary arterial pressure; PH=pulmonary hypertension; PVR=pulmonary vascular resistance; RHC=right heart catheterization; WSPH=World Symposium on Pulmonary Hypertension; WU=Wood units.
The information contained in this section of the site is clinical in nature and specifically created for healthcare professionals. If you are not a US healthcare professional, please click CLOSE to return to the consumer section of the site.